

















How the tetanus shot protects and why boosters are needed
The tetanus shot protects by teaching the immune system to make antibodies that neutralise tetanus toxin, and boosters are needed because those circulating antibodies gradually decline. Those antibodies can act before the toxin binds to nerves.
This explainer examines how tetanus toxoid creates antitoxin immunity, why antibody levels wane, what long-term studies have measured, and why booster schedules differ between public-health systems. It draws on CDC and WHO guidance plus population and follow-up studies published from 2002 to 2026.

Evidence last checked 16 Nov 2026 · 12 min
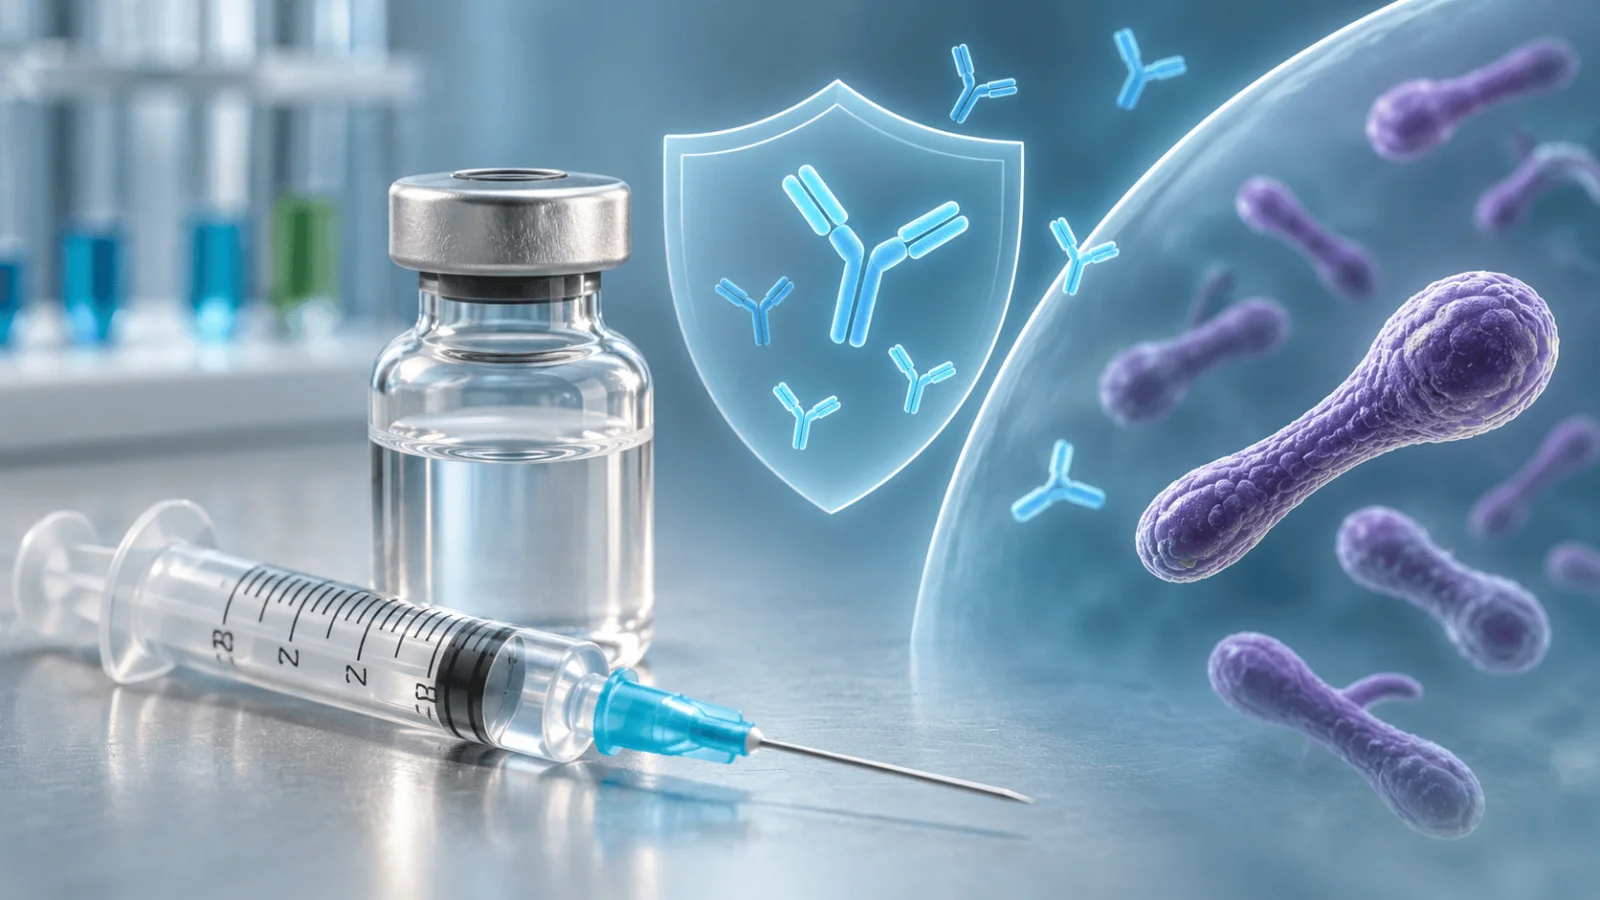
How a tetanus shot turns toxin into an immune target
A tetanus shot does not train the immune system to attack Clostridium tetani bacteria directly. It contains tetanus toxoid, a chemically inactivated form of the bacterium's neurotoxin, so the immune system can recognise the toxin without being exposed to active tetanospasmin. The CDC Pink Book explains that formaldehyde inactivation made tetanus toxoid possible in the 1920s, and modern tetanus-containing vaccines use that same immunological principle in combination products such as DTaP, Tdap and Td (CDC, 2024; CDC, 2026).
After vaccination, antigen-presenting cells process the toxoid and stimulate toxin-specific helper T cells and B cells. Some B cells become plasma cells that release antitoxin antibodies, while others become memory B cells that can respond more rapidly after later exposure or vaccination. The useful endpoint is therefore not an antibody against the bacterial spore itself, but circulating antibody able to bind and neutralise tetanus toxin before the toxin reaches its neural targets.
That distinction matters when vaccine studies are interpreted. A rise in antibody concentration is a laboratory marker with a strong biological link to protection against tetanus, but it is not identical to measuring disease prevention in a randomised efficacy trial. The CDC Pink Book notes that tetanus-toxoid efficacy has not been established through a conventional placebo-controlled vaccine trial and is instead inferred from protective antitoxin concentrations and the rarity of disease after complete vaccination (CDC, 2024). The same need to separate immune markers from clinical protection appears in [historical rabies-vaccine research](/health/uv-inactivated-sheep-brain-rabies-vaccine-health).
How antibodies prevent tetanus before toxin reaches nerves
Tetanus begins when C. tetani spores enter damaged tissue and germinate under favourable low-oxygen conditions. The bacteria release tetanospasmin, which moves from the site of infection and ultimately interferes with inhibitory neurotransmission in the nervous system. CDC describes the result as unopposed muscle contraction and spasm, the basis of the rigidity and convulsive spasms associated with the disease (CDC, 2024).
Vaccine-induced antitoxin works earlier in that chain. Antibodies circulating in blood and extracellular fluid can bind free tetanus toxin and stop it from reaching nerve endings. Once toxin has bound to neural tissue, antibody cannot pull it back out; CDC makes the same distinction when explaining why tetanus immune globulin can neutralise unbound toxin but cannot affect toxin already attached to nerve endings (CDC, 2024).
This explains why antibody concentration matters even though tetanus is caused by a bacterium. Protection depends on having enough neutralising antibody present at the time toxin is produced, not on waiting for a slow primary immune response after contamination has occurred. It also explains why recovering from tetanus does not reliably create immunity: the amount of toxin capable of causing severe disease is too small to provide a dependable immunising exposure, so previous illness does not substitute for vaccination (CDC, 2024; WHO, 2026).
Why the primary series matters before boosters
A booster is not a substitute for the initial vaccine series. The first doses establish the immune response and increase the pool of toxin-specific B cells, while later doses raise antibody concentration and strengthen the persistence of that response. In the CDC Pink Book, a properly spaced three-dose primary series in adults, or the corresponding childhood series followed by a booster, produces antitoxin concentrations above the protective level in essentially all recipients (CDC, 2024). That is why studies of booster duration are most informative when participants have a documented primary series rather than an uncertain vaccination history.
The distinction between priming and boosting also helps explain why one dose cannot be interpreted in isolation. An antibody measurement after a recent booster reflects both the new dose and the immune history built by earlier doses. Tomovici and colleagues, for example, followed people who had already been primed before receiving the Tdap booster studied in their trials; the persistence observed 10 years later therefore represents a recalled immune response, not protection generated by a first-ever exposure to tetanus toxoid (Tomovici et al., 2012).
At population level, incomplete records blur this picture. Chen and colleagues used documented dose histories when modelling antibody trajectories in Zhejiang and excluded recall-only vaccination information from analyses that required exact dose timing (Chen et al., 2026). Their results showed higher antibody concentrations after documented vaccination but also substantial variation by dose category and time since the last dose. This is one reason guideline schedules are organised around a complete series plus boosters rather than around a single antibody result.
Why immune memory is not the same as circulating antitoxin
Memory B cells and circulating antibody answer different timing problems. Memory can generate a strong secondary response after the immune system encounters toxoid again, whereas neutralising antibody is already present and can act immediately against free toxin. Because tetanospasmin becomes inaccessible to antibody after binding to nerve endings, the protective margin at the moment of exposure matters. This does not mean that a single antibody threshold perfectly predicts an individual outcome, but it explains why schedules aim to keep antitoxin from drifting too low between doses rather than assuming that memory alone is always fast enough.
The laboratory thresholds used in studies are therefore useful population tools, not a stopwatch. WHO notes that 0.01 IU/mL is generally considered the minimum protective level when antitetanus antibody is measured by toxin-neutralisation methods, whereas validated ELISA assessments usually use a higher threshold around 0.1 IU/mL (WHO, 2014). A person can therefore be above one study cut-off and below another, so apparent disagreement between studies may reflect the assay and endpoint as much as biology. Comparing results requires keeping the assay and threshold attached to every percentage and duration estimate.
Why protection decreases after vaccination
Antibody levels are highest after a primary series or booster and then decline. Long-lived plasma cells can continue producing antibody for years, and memory cells remain available for a faster response, but the concentration of circulating antitoxin is not fixed for life in every person. This falling concentration is the biological reason booster doses are used: a booster re-exposes the immune system to toxoid and raises antitoxin levels before they become too low in a meaningful share of the population.
The size and speed of that decline differ between studies because populations, vaccine histories, assays and definitions of protection differ. Hammarlund and colleagues measured tetanus and diphtheria antibodies in 546 adults. The tetanus-antibody half-life estimate of 14 years, with a 95% confidence interval of 11 to 17 years, was based on 392 participants for whom time-since-vaccination data were available; about 97% of the full cohort were seropositive at a threshold of at least 0.01 IU/mL (Hammarlund et al., 2016). Their mathematical model predicted that 95% of the population would remain seroprotected against tetanus for at least 30 years, a result that prompted the authors to question routine 10-year adult boosters.
An older national US serosurvey produced a less reassuring population picture. McQuillan and colleagues analysed serum from 18,045 people examined in 1988–1994 and found tetanus antibody above their protective threshold of 0.15 IU/mL in 72.3% overall; the proportion was about 31% among people aged 70 years (McQuillan et al., 2002). That study reflects an earlier vaccination era and used a different threshold, so it should not be treated as a direct contradiction of the 2016 study, but it shows why age and vaccination history matter when population protection is estimated.
What long-term booster studies actually show
A 10-year follow-up by Tomovici and colleagues tracked antibody persistence after a Tdap booster in adolescents and adults originally enrolled in clinical trials. The source cohorts comprised 324 adolescents and 644 adults, although only subsets contributed samples at the 10-year time point. Among adolescents tested at 10 years, 100% had tetanus antitoxin concentrations of at least 0.01 IU/mL and more than 99% had concentrations of at least 0.1 IU/mL; tetanus responses in adults were described as similar to those in adolescents (Tomovici et al., 2012). The study supports long persistence after boosting, but attrition at the 10-year follow-up limits how directly those measurements represent the original cohorts and it does not establish that every individual remains protected indefinitely.
A newer cross-sectional study in Zhejiang, China, adds a different population and a stricter ELISA seroprotection threshold. Chen and colleagues measured tetanus IgG in 3,659 healthy participants aged up to 59 years in 2024 and reported 85.05% seropositivity at least 0.01 IU/mL but 52.94% seroprotection at least 0.1 IU/mL (Chen et al., 2026). Their waning analysis was restricted to participants with verifiable documented vaccination dates; in that analysis, modelled antibody trajectories remained above 0.1 IU/mL for approximately 8.81 years overall. The estimate varied with dose history and subgroup, and the authors warned that a high seropositivity rate does not necessarily mean durable seroprotection.
These studies cannot be stacked into one universal countdown because they ask related but different questions. Hammarlund et al. used a lower threshold and modelled persistence in vaccinated US adults; Tomovici et al. followed selected trial participants after a known booster; Chen et al. reconstructed population trajectories under a Chinese immunisation programme and used 0.1 IU/mL as the seroprotection cut-off. The table summarises those differences rather than treating the reported years as interchangeable.
Study | Population and design | Threshold or endpoint | Main finding | Important limit |
McQuillan et al. 2002 | 18,045 US participants, cross-sectional NHANES 1988–1994 | Protective tetanus antibody >0.15 IU/mL | 72.3% protected overall; about 31% at age 70 | Older vaccination era and single-time-point serology |
Tomovici et al. 2012 | 324 adolescent and 644 adult source cohorts; subsets sampled at year 10 | Tetanus antitoxin at >=0.01 and >=0.1 IU/mL after booster | At 10 years, 100% of tested adolescents were >=0.01 IU/mL and >99% were >=0.1 IU/mL; adult tetanus responses similar | Selected trial cohorts with substantial attrition by year 10 |
Hammarlund et al. 2016 | 546 US adults, cross-sectional; half-life estimate based on 392 with time-since-vaccination data | Seropositive >=0.01 IU/mL | About 97% seropositive; estimated tetanus-antibody half-life 14 years | Modelled persistence depends on threshold and assumptions |
Chen et al. 2026 | 3,659 healthy people in Zhejiang, cross-sectional 2024; waning model limited to verified vaccination dates | Seropositive >=0.01; seroprotected >=0.1 IU/mL | 85.05% seropositive; 52.94% seroprotected; modelled 8.81 years above 0.1 overall | Different programme, assay and reconstructed dose histories |
The tetanus shot protects by keeping neutralising antitoxin available before toxin binds to nerves. Boosters restore that margin, but the ideal adult interval is a policy question, not a universal biological expiry date.
Why booster schedules differ between guidelines
Public-health schedules translate immunology into policy, and policy includes more than antibody decay. For routine adult vaccination, the US CDC recommends continuing tetanus-containing boosters after the primary series, with timing defined in its adult schedule (CDC, 2025); vaccination may also be indicated sooner for some wounds (CDC, 2026). ACIP also concluded that repeat Tdap was safe and immunogenic at the intervals studied and has allowed either Td or Tdap for subsequent adult booster vaccination in people who have already received Tdap (Havers et al., 2020).
WHO takes a life-course approach designed for global immunisation programmes. Its 2017 position paper recommends a life-course schedule across childhood and adolescence, with the goal of lifelong protection; the WHO tetanus fact sheet retained this framework in 2026 (WHO, 2017; WHO, 2026). The difference does not mean that one organisation accepts waning immunity and the other rejects it. They are different programme recommendations: WHO provides global guidance built around a life-course childhood-to-adolescence schedule, while CDC recommends continuing tetanus-containing boosters for US adults according to its adult schedule.
Wound guidance adds another layer because CDC aims to ensure adequate circulating antitoxin after injuries with greater tetanus risk. The CDC Pink Book notes that a small percentage of people can fall below the minimal protective antitoxin level before 10 years, and CDC's September 2026 clinical guidance therefore uses both wound type and vaccination history when deciding whether tetanus vaccination is indicated, including a shorter interval for dirty or major wounds than for clean, minor wounds (CDC, 2024; CDC, 2026). This is a clinical decision framework, not evidence that immunity disappears suddenly on a particular anniversary. A similar distinction between vaccine evidence and policy history is discussed in [the site's polio vaccine explainer](/health/the-present-status-of-polio-vaccines-health).
What is proven about tetanus protection and what remains uncertain
Several conclusions are well supported. Tetanus toxoid induces antitoxin antibodies; a complete primary series produces protective antibody levels in almost all recipients; circulating antibody declines over time; and a booster can raise antibody again (CDC, 2024; Tomovici et al., 2012). Tetanus itself does not reliably immunise a person, and prevention depends on vaccination because the disease is caused by a potent toxin that can act before a new primary immune response would be useful (CDC, 2024; WHO, 2026).
The uncertainty concerns the optimal routine adult interval, not whether the vaccine works. Long-term serology studies suggest that many vaccinated adults retain measurable or protective antibody well beyond 10 years, but the exact proportion depends on threshold, assay, age, previous doses and population history (Hammarlund et al., 2016; Chen et al., 2026). Clinical tetanus is also rare in highly vaccinated populations (WHO, 2026), and CDC notes that tetanus-toxoid efficacy has never been studied in a vaccine trial (CDC, 2024).
For that reason, a booster schedule should be read as a population policy rather than a laboratory expiration date for immunity. The evidence supports maintaining antitoxin protection across the life course, while the spacing used to achieve that goal legitimately differs between health systems. The most defensible summary is that boosters restore waning antibody, but research has not identified one interval that is demonstrably necessary for every fully vaccinated adult in every setting.
- Well established: tetanus toxoid generates neutralising antitoxin, and complete vaccination produces protective antibody in nearly all recipients.
- Well established: antibody concentrations decline with time and rise again after booster vaccination.
- Not settled: one routine adult booster interval that is optimal for every population, vaccine history and health system.
- Context dependent: recommendations after wounds use exposure risk and documented vaccination history as well as time since the last dose.
Frequently asked questions
How long does protection from a tetanus shot last?
Protection can persist for many years after a completed series, but it does not decline at the same speed in everyone. Follow-up found tetanus antibody persistence at 10 years, while population studies showed wider variation in protective levels (Tomovici et al., 2012; Hammarlund et al., 2016). Booster policy therefore uses population margins rather than an exact expiry date.
Why are boosters used if the immune system has memory?
Immune memory can produce a faster secondary response, but circulating antitoxin is already present when exposure occurs. Tetanus toxin can bind to nerve endings before a delayed antibody rise is complete. Boosters raise the antibody level in advance, increasing the chance that free toxin is neutralised before it reaches neural tissue.
Is a tetanus shot the same as Tdap?
Tdap is one type of tetanus-containing vaccine. It also protects against diphtheria and pertussis, while Td contains tetanus and diphtheria components. In the United States, CDC allows either Td or Tdap for routine adult tetanus boosters after a person has received the recommended Tdap dose, depending on age and vaccination history.
Can fully vaccinated people still develop tetanus?
Yes, but it is uncommon. CDC notes that tetanus cases have rarely occurred in people with a documented complete primary series, and protective antitoxin levels are achieved in almost all properly vaccinated recipients. No vaccine produces identical antibody persistence in every person, which is one reason schedules include boosters and exposure-based guidance.
Does having tetanus once make a person immune?
No. Tetanus disease does not reliably create protective immunity because an extremely small amount of toxin can cause illness without providing enough antigen to build dependable long-term protection. CDC and WHO therefore treat previous tetanus illness as different from vaccination; recovery does not by itself establish future immunity against another exposure.
Sources
- Centers for Disease Control and Prevention. Tetanus Vaccination. 10 September 2026. https://www.cdc.gov/tetanus/vaccines/index.html
- Centers for Disease Control and Prevention. Chapter 21: Tetanus. Epidemiology and Prevention of Vaccine-Preventable Diseases (Pink Book). 25 April 2024. https://www.cdc.gov/pinkbook/hcp/table-of-contents/chapter-21-tetanus.html
- Centers for Disease Control and Prevention. Clinical Guidance for Wound Management to Prevent Tetanus. 8 September 2026. https://www.cdc.gov/tetanus/hcp/clinical-guidance/
- World Health Organization. Tetanus. Fact sheet. 15 July 2026. https://www.who.int/news-room/fact-sheets/detail/tetanus
- World Health Organization. Tetanus vaccines: WHO position paper - February 2017. Weekly Epidemiological Record. 2017;92(6):53–76. https://www.who.int/publications/i/item/who-wer9206
- Hammarlund E, Thomas A, Poore EA, et al. Durability of Vaccine-Induced Immunity Against Tetanus and Diphtheria Toxins: A Cross-sectional Analysis. Clinical Infectious Diseases. 2016;62(9):1111–1118. DOI 10.1093/cid/ciw066. https://academic.oup.com/cid/article/62/9/1111/1745278
- Tomovici A, Barreto L, Zickler P, Meekison W, Noya F, Voloshen T, Lavigne P. Humoral immunity 10 years after booster immunization with an adolescent and adult formulation combined tetanus, diphtheria, and 5-component acellular pertussis vaccine. Vaccine. 2012;30(16):2647–2653. DOI 10.1016/j.vaccine.2012.02.013. https://pubmed.ncbi.nlm.nih.gov/22353673/
- Chen F, Zhou Y, Zhu Y, Pan X, Ding L, He H, Qi X. Population waning trajectories of vaccine-induced tetanus immunity in Zhejiang, China. Frontiers in Immunology. 2026;17:1824381. DOI 10.3389/fimmu.2026.1824381. https://pmc.ncbi.nlm.nih.gov/articles/PMC13243430/
- McQuillan GM, Kruszon-Moran D, Deforest A, Chu SY, Wharton M. Serologic immunity to diphtheria and tetanus in the United States. Annals of Internal Medicine. 2002;136(9):660–666. DOI 10.7326/0003-4819-136-9-200205070-00008. https://pubmed.ncbi.nlm.nih.gov/11992301/
- Havers FP, Moro PL, Hunter P, Hariri S, Bernstein H. Use of Tetanus Toxoid, Reduced Diphtheria Toxoid, and Acellular Pertussis Vaccines: Updated Recommendations of the Advisory Committee on Immunization Practices - United States, 2019. MMWR Morbidity and Mortality Weekly Report. 2020;69:77–83. DOI 10.15585/mmwr.mm6903a5. https://www.cdc.gov/mmwr/volumes/69/wr/mm6903a5.htm
- Centers for Disease Control and Prevention. Adult Immunization Schedule Notes: Recommendations for Ages 19 Years or Older, United States, 2025. 2 July 2025. https://www.cdc.gov/vaccines/hcp/imz-schedules/adult-notes.html
- World Health Organization. Recommendations to assure the quality, safety and efficacy of tetanus vaccines (adsorbed), Annex 5. WHO Technical Report Series No. 980. 2014. https://cdn.who.int/media/docs/default-source/biologicals/vaccine-standardization/tetanus/tetanus_recommendations_trs_980_annex_5.pdf

Elias Norford — author,editor
Elias trained in biomedical science before completing postgraduate study in epidemiology, where he developed a particular interest in study design, population risk, disease surveillance and the interpretation of health data. He later moved into non-clinical re...
This article is for general information and is not medical advice. It was reviewed for accuracy by a qualified clinician; decisions about your health should be made with your own doctor.
Related

Polio vaccines in 1960: what the debate got right and wrong

UV-Inactivated Sheep-Brain Rabies Vaccine: A 1975 Experiment

Prophylactic Inoculations and Poliomyelitis: 620 Victorian Cases
How Graves’ disease antibodies push the thyroid into overdrive
Psoriatic arthritis and why a skin condition affects the joints
How myasthenia gravis antibodies block nerve signals to muscles
What autoimmune disease is and why the immune system attacks the body
