
















What autoimmune disease is and why the immune system attacks the body
Autoimmune disease occurs when the immune system responds to the body's own cells or tissues because the mechanisms that normally restrain self-directed reactions are no longer sufficient. The consequences vary between disorders: antibodies, T cells and failures of immune regulation may contribute in different ways, affecting particular organs or several body systems.
To explain how this happens, the article examines the safeguards that normally control immune responses, the roles of inherited susceptibility and external exposures, and the difficulties involved in recognising different autoimmune disorders. It draws on mechanistic research, the National Academies' 2022 evidence assessment and clinical information published by public medical institutions.

Evidence last checked 9 Nov 2026 · 13 min
What is an autoimmune disease?
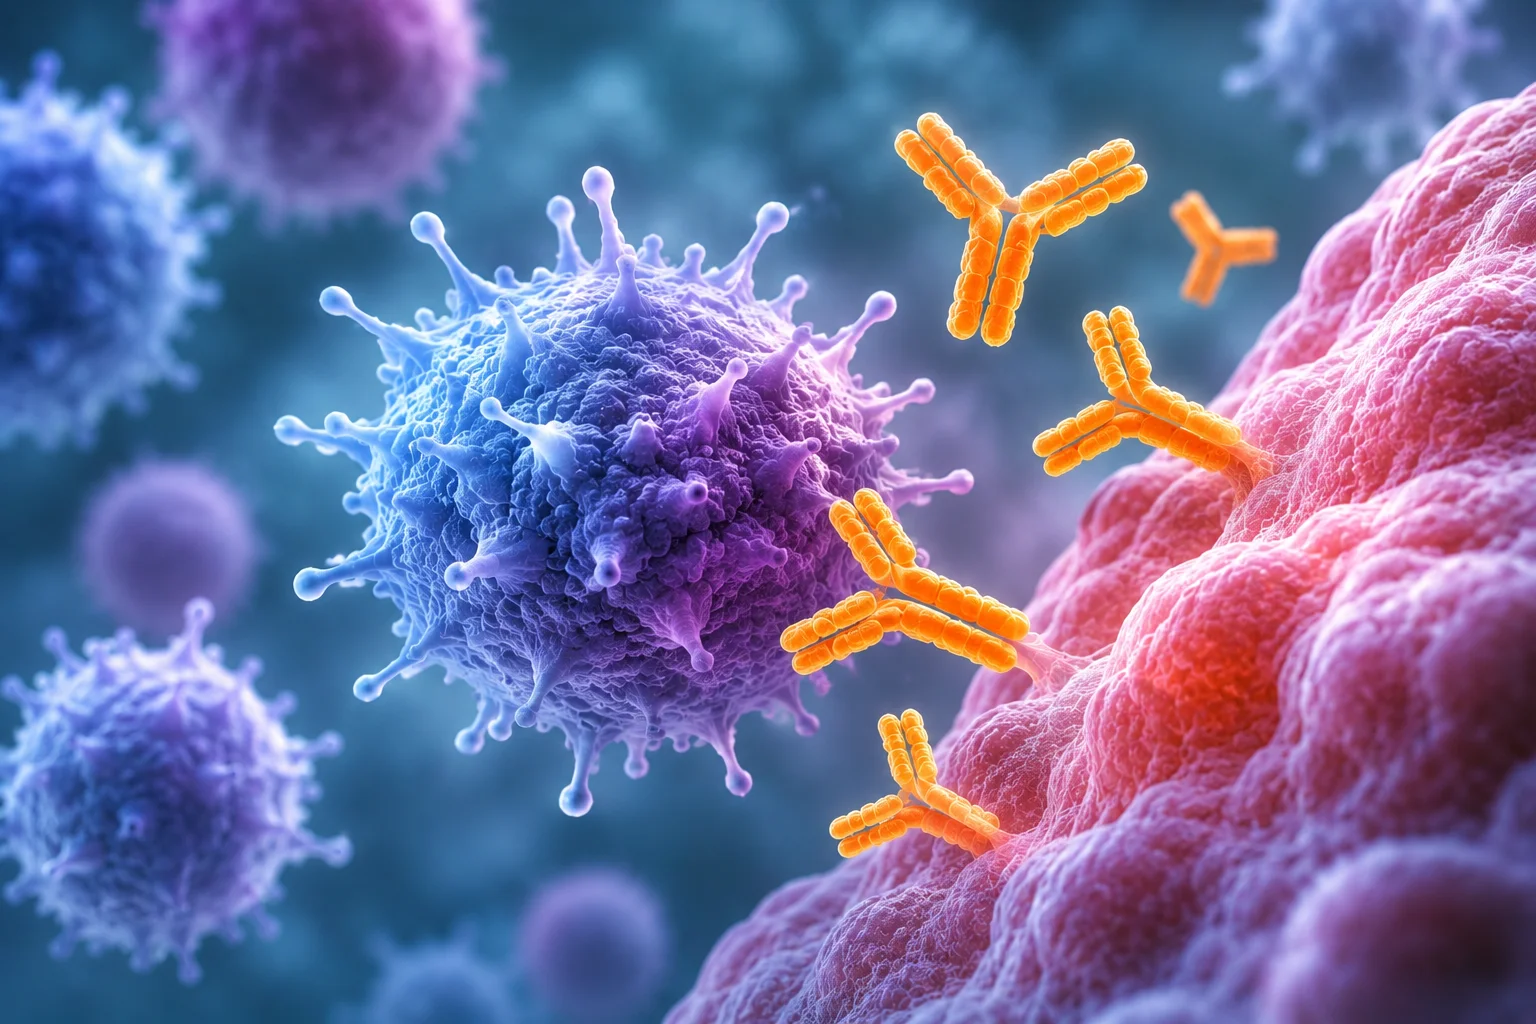
In autoimmune conditions, protective immune responses become directed towards structures belonging to the body rather than external pathogens. This can disturb normal organ function through inflammation, injury to particular cells or other immune-mediated effects. The outcome depends on the tissue involved and the processes responsible for the reaction, as described in the National Institutes of Health overview (NIH, 2022).
The term covers numerous distinct illnesses rather than one disease with a predictable clinical course. Depending on how researchers define and group individual conditions, estimates range from more than 80 to approximately 150 (National Academies of Sciences, Engineering, and Medicine, 2022). Some predominantly involve one tissue or organ, while others can affect multiple systems. Their causes, symptoms and long-term outcomes cannot therefore be described accurately using a single universal pattern.
Autoimmune disease also differs from an allergy or an immunodeficiency. An allergic response is directed against a normally harmless external substance; an immunodeficiency means that protective immune function is absent or reduced. Autoimmunity concerns an inappropriate response to the body's own structures, although some people may have overlapping immune problems.
The National Institute of Arthritis and Musculoskeletal and Skin Diseases describes this distinction through examples involving joints, skin and multiple organs (NIAMS, 2023). The distinction between protective immunity and autoimmunity is also relevant to [experimental rabies-vaccine research](/health/uv-inactivated-sheep-brain-rabies-vaccine-health), where investigators measured antibodies directed against a virus rather than the body's own tissues.
The detection of an immune marker does not necessarily indicate an autoimmune illness. Autoantibodies may be present in people without a diagnosed condition, while inflammation can also result from infection, injury or other processes. To determine whether a finding has clinical importance, it must be considered alongside symptoms, the organs involved and additional investigations. This distinction is particularly important when interpreting laboratory results and estimates of disease frequency.
Why does the immune system attack healthy tissue?
Preventing harmful reactions against the body's own structures requires several layers of immune control, collectively described as tolerance. Autoimmune disorders may arise when these controls fail to remove, inactivate or adequately restrain self-reactive lymphocytes. Rosenblum, Remedios and Abbas (2015) explain that the central problem is the loss of effective regulation over particular immune responses, not a general increase in the strength of the immune system.
How immune tolerance normally works
During immune-cell development, many cells that strongly recognise self-components are removed or altered before they can circulate widely. Other potentially self-reactive cells remain but are normally held in check by regulatory pathways and the absence of appropriate activation signals. These controls operate at different stages, so failure at one stage does not produce the same disease in every person. The balance between cells that promote inflammation and cells that restrain it is central to the model outlined by Rosenblum and colleagues (2015).
B cells can produce antibodies that bind specific targets, while T cells can coordinate inflammation or directly damage cells. In some autoimmune diseases, autoantibodies are important contributors to injury; in others, T-cell-driven processes or combinations of mechanisms are more prominent. An antibody in the blood is therefore neither a complete description of the disease nor proof of the exact process taking place in a tissue. The type of immune response matters as much as its presence.
Why inflammation may continue
Once an autoimmune response has begun, tissue injury can expose additional self-components and sustain immune activation. Inflammatory signals can recruit further cells and alter how the affected organ works, producing cycles of activity that are difficult to predict. Some conditions alternate between more active periods and remission, while others progress gradually. Rosenblum and colleagues (2015) discuss initiation, propagation and periods of relative resolution as distinct features of autoimmune reactions.
An inflammatory response is not inherently abnormal; its purpose and consequences depend on what it targets. In autoimmunity, the target belongs to the person rather than an invading organism.
The effects then differ according to the affected tissue. Joint inflammation can restrict movement, damage to a hormone-producing gland can alter its function, and inflammation involving the nervous system can interfere with communication between cells. These consequences are not interchangeable, even when a failure of immune tolerance contributes to each.
What causes autoimmune disease, and who is at risk?
The development of autoimmunity cannot be traced to one initiating event shared by every patient. Susceptibility may exist long before symptoms appear, while exposures proposed as triggers are not equally well supported for every diagnosis.
The National Academies (2022) emphasised that evidence across autoimmune diseases remains uneven, particularly when research attempts to connect environmental exposures with subsequent illness. Three questions therefore need to be considered separately: what increases susceptibility, what may initiate an abnormal immune response, and what allows disease activity to continue. An association found in a population cannot necessarily answer all three.
Genes, family history and sex differences
Family history can indicate a predisposition to autoimmunity, but it cannot establish which illness a person will develop or whether illness will occur at all. Relatives may experience different autoimmune conditions because inherited variation influences several aspects of immune recognition and regulation. These genetic influences interact with factors outside the genome.
NIEHS (2026) describes this relationship, helping explain why neither family history nor a genetic finding can independently predict an autoimmune diagnosis. A different example of inherited biological variation appears in [research on human blood-group genetics](/health/human-blood-group-distribution-population-genetics-research), which examines how inherited blood-cell markers vary between populations without treating those markers as predictors of autoimmune disease.
The distribution of autoimmune illnesses differs between sexes, although the pattern is far from uniform. Female patients account for a larger share of diagnoses in several disorders, while other conditions show much smaller differences. The National Institutes of Health (2024) reports that researchers have not fully explained why many autoimmune diseases occur more often in women. Investigations consider the effects of sex hormones, inherited characteristics and immune regulation, but these influences do not provide one explanation that applies to every autoimmune diagnosis.
Infections and environmental exposures
The relationship between infection and subsequent autoimmunity is particularly well studied in multiple sclerosis. Bjornevik and colleagues (2022) examined longitudinal data from United States military personnel and found a strong association between earlier Epstein–Barr virus infection and later multiple sclerosis.
This evidence supports an important role for the virus in that particular disease. However, Epstein–Barr virus infects a large proportion of the population, while relatively few people develop multiple sclerosis. Infection alone therefore cannot explain why the condition emerges in some individuals.
The Epstein–Barr virus result cannot be used to explain rheumatoid arthritis, thyroid autoimmunity or every other autoimmune condition. Nor does a strong association identify all of the biological steps connecting exposure to disease. Other proposed influences include smoking and certain occupational or environmental exposures, but the quality of evidence varies. The National Academies (2022) called for more consistent long-term research to separate genuine causes from factors that merely accompany illness.
What are common autoimmune diseases and symptoms?
The clinical picture depends heavily on the location of immune-related injury. A thyroid disorder, inflammatory arthritis and a condition involving the central nervous system can share an autoimmune basis while producing very different symptoms and investigation results.
Some illnesses remain concentrated in one organ; others involve several systems. The National Academies (2022) identified this diversity as a challenge when estimating the overall burden of autoimmune illness. Consequently, a general symptom list cannot reliably describe every condition or substitute for disease-specific assessment.
In rheumatoid arthritis, clinicians consider whether joint complaints form a recognisable inflammatory pattern rather than focusing on pain alone. Stiffness and swelling often affect corresponding joints on both sides, although the disease can also involve structures outside the joints, including the lungs and eyes (NIAMS, 2022). Such findings provide useful diagnostic clues, but they do not independently confirm rheumatoid arthritis. Their significance depends on the history of symptoms, examination results and other evidence.
Lupus does not follow an identical clinical course in every patient. Skin changes, joint problems, kidney involvement and abnormalities affecting blood cells may occur in different combinations, and their intensity can rise or fall over time. The CDC's account of lupus highlights how this variation can make the illness difficult to recognise (CDC, 2024). Two people with lupus may therefore experience very different clinical manifestations.
Hashimoto's disease provides an example of how an autoimmune process can lead to problems primarily through reduced organ function. Immune-mediated changes affect the thyroid, and an important clinical consequence is its declining ability to produce sufficient hormones. NIDDK (2021) describes the immune findings associated with this condition. Tiredness and sensitivity to cold may result from thyroid dysfunction, although neither symptom identifies Hashimoto's disease without additional clinical and laboratory evidence.
The site of immune injury changes the consequences of disease. In type 1 diabetes, destruction of pancreatic cells reduces insulin production; in multiple sclerosis, inflammatory processes affect structures of the central nervous system. Their symptoms and diagnostic pathways are therefore not interchangeable. NIH (2022) presents these conditions as examples of the wide clinical range covered by the term autoimmune disease.
How examples differ by tissue
Condition | Main tissue or system | Illustrative consequence |
Rheumatoid arthritis | Joint lining | Pain, swelling and stiffness (NIAMS, 2022) |
Lupus | Multiple organs | Variable systemic features (CDC, 2024) |
Hashimoto's disease | Thyroid | Reduced hormone production (NIDDK, 2021) |
Multiple sclerosis | Central nervous system | Inflammatory damage to nerve pathways (NIH, 2022) |
How is an autoimmune disease diagnosed?
Diagnosis begins with a clinical pattern, not with a single universal laboratory result. Clinicians consider the timing and distribution of symptoms, examination findings, family and medical history, and whether another condition offers a better explanation. Tests are then selected according to the organs and mechanisms suspected. The National Academies (2022) identified diagnostic complexity and inconsistent disease definitions as persistent challenges in autoimmune research and care.
What autoantibody tests can and cannot show
An antinuclear antibody, or ANA, test detects antibodies that react with components of cell nuclei. It can be useful when the clinical picture suggests certain systemic autoimmune conditions, but a positive result is not a diagnosis. MedlinePlus explains that ANA can also be found in healthy people and in some other illnesses, while a negative result does not exclude every autoimmune disorder (MedlinePlus, 2025).
Interpretation depends on the broader clinical context. The importance of interpreting antibody tests in context is also illustrated by [research on cardiolipin-based syphilis serology](/health/cardiolipin-standardization-syphilis-serology-health), where a reactive laboratory result alone cannot establish a diagnosis.
Some antibody assays are useful for investigating a specific suspected disorder, but results cannot be interpreted independently of the patient's clinical presentation. The testing method, reference interval and likelihood of disease before testing all affect how much weight a result carries. In people without compatible symptoms, broad testing may uncover positive findings that have little diagnostic significance. An abnormal result, by itself, does not demonstrate organ-directed autoimmunity.
Why different conditions require different evidence
What counts as persuasive evidence varies by suspected disease. An investigation of thyroid autoimmunity considers thyroid hormone measurements together with relevant antibodies, whereas suspected inflammatory arthritis calls for examination of affected joints and, where appropriate, additional investigations. NIDDK (2021) and NIAMS (2022) describe different diagnostic approaches for these conditions. Neither testing strategy can be applied unchanged to the other, because the organs affected and the underlying clinical questions are different.
Some autoimmune conditions have fluctuating activity, so results and symptoms may differ between assessments. Others share features with infections, metabolic conditions or non-autoimmune inflammatory disorders. The challenge is not simply detecting inflammation but identifying its cause and consequences. A sound explanation of diagnosis therefore distinguishes a screening clue, a supporting finding and evidence sufficient for a particular diagnosis.
A laboratory result answers a narrower question than a diagnosis. For example, an ANA finding may contribute to the assessment of suspected systemic autoimmunity, but it does not identify which organ is affected or whether symptoms have an autoimmune cause. A negative ANA result also cannot exclude every immune-mediated disorder.
Thyroid investigations illustrate a different distinction: measurements of gland function describe what the thyroid is doing, whereas thyroid-directed antibodies provide information about a possible immune mechanism. Neither type of result, considered in isolation, explains the full clinical picture. MedlinePlus (2025) and NIDDK (2021) describe these different uses of testing. Read together, their guidance shows why the significance of an abnormal result depends on the question the test was chosen to answer, rather than on the words positive or negative alone.
What does research establish, and what remains uncertain?
Research firmly establishes that autoimmune diseases involve misdirected immune responses, but it does not support one universal cause or a single diagnostic marker. The mechanistic review by Rosenblum and colleagues (2015) explains how failures of tolerance can contribute to disease, while the National Academies (2022) documents important differences between conditions and gaps in population data. These sources answer different questions: one concerns biological mechanisms, the other the breadth and limits of the evidence base.
The number of recognised autoimmune diseases is itself an example of uncertainty rather than a fixed biological constant. The National Academies (2022) reported estimates ranging from more than 80 to about 150, depending on the definition used. Similarly, population prevalence estimates differ according to which diagnoses are counted and how cases are identified. A figure drawn from one registry or a narrow disease list should not be presented as the definitive frequency of all autoimmune disease.
The sources also answer different kinds of scientific questions, which should not be confused. Rosenblum, Remedios and Abbas (2015) examine how immune tolerance can break down at the cellular level; their account helps explain mechanisms but does not measure how frequently particular diseases develop.
Bjornevik and colleagues (2022) provide a different kind of evidence by examining the timing of Epstein–Barr virus infection before multiple sclerosis in a longitudinal population. That sequence strengthens an argument about a disease-specific risk factor, without explaining every step in the biological pathway. The National Academies (2022), meanwhile, assess why estimates across the broader autoimmune field remain difficult to compare when disease definitions and study populations differ. Together, these works demonstrate why a convincing explanation may require laboratory evidence, long-term observation and careful population definitions, rather than treating any one approach as sufficient.
The study of infections shows why the strength of evidence must be judged disease by disease. Bjornevik and colleagues (2022) followed a large cohort and found that Epstein–Barr virus infection was strongly associated with subsequent multiple sclerosis. That result does not mean all infected people will develop the disease, and it does not establish an equivalent mechanism for other autoimmune conditions. Conclusions about one diagnosis cannot automatically be extended to another.
Autoimmune disorders share a breakdown in the control of self-directed immune responses, but their causes, affected tissues and diagnostic evidence differ substantially.
Clinical outcomes also vary. Some diseases remain largely confined to one organ, while others can produce complications in several systems; periods of remission and increased activity are possible in some conditions. The CDC's 2024 lupus overview illustrates this variability, while NIAMS (2022) describes the different pattern seen in rheumatoid arthritis. Comparing these examples helps explain why general descriptions must leave room for disease-specific exceptions.
What is the main conclusion about autoimmune disease?
Autoimmune disease develops when immune responses are directed against the body's own tissues and normal controls fail to prevent harmful activity. This broad mechanism is well established, but it does not identify which disease a person has or why that disease developed. The strongest explanations connect immune biology to the affected organ, the clinical pattern and disease-specific evidence. NIH (2022) and Rosenblum and colleagues (2015) support this distinction between the general principle and individual mechanisms.
The available evidence supports contributions from inherited susceptibility and environmental influences, with clear differences among conditions. For some questions, such as the association between Epstein–Barr virus and multiple sclerosis, prospective research has substantially strengthened causal understanding. For many others, the precise sequence of events remains uncertain. The National Academies (2022) identifies these unresolved questions as priorities for further investigation.
A useful account of autoimmunity therefore separates what is known from what is merely suspected. An abnormal antibody result is not automatically a disease, a shared symptom is not a diagnosis, and a risk factor is not a prediction for an individual. Those boundaries are essential to explaining autoimmune disease accurately without turning a general health article into personal diagnostic or treatment instructions.
Frequently asked questions
Can a positive ANA test occur without an autoimmune disease?
Yes. Antinuclear antibodies may be found in otherwise healthy people, and their presence alone does not identify a particular illness. MedlinePlus explains that interpretation depends on symptoms and other findings. The clinical significance of a result varies with the test method, the individual and the condition being investigated.
Are autoimmune diseases always passed down through families?
No. Inherited susceptibility can contribute to autoimmune disease, but most conditions do not follow a simple inheritance pattern. Environmental influences and immune regulation also matter. A family history may alter risk without making illness inevitable, and the relative contribution of genetic factors differs substantially between autoimmune diagnoses.
Can one person have more than one autoimmune condition?
Yes. Autoimmune diseases can occur together in the same person, although the combinations and frequencies vary. The National Academies' 2022 review identifies overlap between diagnoses as one reason these conditions are challenging to study as a group. The presence of one disease does not automatically establish another.
Do autoimmune symptoms always remain constant?
No. Some autoimmune conditions fluctuate, with periods of greater activity and periods of relative improvement. Others cause more persistent problems or gradual changes in organ function. The pattern depends on the disease and the tissues affected. Fluctuation is not specific to autoimmunity and cannot establish a diagnosis by itself.
Does having Epstein–Barr virus mean someone will develop multiple sclerosis?
No. Epstein–Barr virus infection is common, whereas multiple sclerosis is much less common. Bjornevik and colleagues (2022) found a strong association between infection and later multiple sclerosis in a large cohort, but infection alone was not sufficient to explain who developed disease. Other susceptibility factors remain important.
Sources
- National Academies of Sciences, Engineering, and Medicine. Enhancing NIH Research on Autoimmune Disease. National Academies Press, 2022. DOI: 10.17226/26554.
- Rosenblum, M. D., Remedios, K. A., and Abbas, A. K. Mechanisms of human autoimmunity. Journal of Clinical Investigation, 2015;125(6):2228–2233. DOI: 10.1172/JCI78088.
- National Institutes of Health (NIH). Understanding Autoimmune Diseases. NIH News in Health, June 2022. https://newsinhealth.nih.gov/2022/06/understanding-autoimmune-diseases
- National Institute of Arthritis and Musculoskeletal and Skin Diseases (NIAMS). Autoimmune Diseases. National Institutes of Health, Last reviewed March 2023. https://www.niams.nih.gov/health-topics/autoimmune-diseases
- National Institute of Environmental Health Sciences (NIEHS). Autoimmune Diseases. National Institutes of Health, Last reviewed 6 March 2026. https://www.niehs.nih.gov/health/topics/conditions/autoimmune
- National Institutes of Health (NIH). Understanding sex differences in autoimmune disease. NIH Research Matters. 13 February 2024. https://www.nih.gov/news-events/nih-research-matters/understanding-sex-differences-autoimmune-disease
- Bjornevik, K., et al. Longitudinal analysis reveals high prevalence of Epstein-Barr virus associated with multiple sclerosis. Science, 2022;375(6578):296–301. DOI: 10.1126/science.abj8222.
- National Institute of Arthritis and Musculoskeletal and Skin Diseases (NIAMS). Rheumatoid Arthritis. National Institutes of Health, Last reviewed November 2022. https://www.niams.nih.gov/health-topics/rheumatoid-arthritis
- Centers for Disease Control and Prevention (CDC). Lupus Basics. 15 May 2024. https://www.cdc.gov/lupus/about/index.html
- National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK). Hashimoto's Disease. National Institutes of Health, Last reviewed June 2021. https://www.niddk.nih.gov/health-information/endocrine-diseases/hashimotos-disease
- MedlinePlus. ANA (Antinuclear Antibody) Test. National Library of Medicine, 19 March 2025. https://medlineplus.gov/lab-tests/ana-antinuclear-antibody-test/

Nora Veldin — author
Nora Veldin is a health science writer with academic training in biomedical science and public health. After completing a BSc in Biomedical Science, she undertook an MPH focused on epidemiology, population health and the interpretation of health evidence. Her...
This article is for general information and is not medical advice. It was reviewed for accuracy by a qualified clinician; decisions about your health should be made with your own doctor.
Related

UV-Inactivated Sheep-Brain Rabies Vaccine: A 1975 Experiment

Human blood groups and population genetics in Mourant’s atlas

How Cardiolipin Helped Standardize Syphilis Serology

Perimenopause symptoms and the hormone changes behind them
How staph infections start on the skin and reach the blood

How exercise affects self-concept and well-being in midlife

How RSV spreads: lessons from a 1981 transmission study
