

















Common cold symptoms and why rhinoviruses cause them
Common cold symptoms include a runny or blocked nose, sneezing, a sore throat and cough. They develop when respiratory viruses infect the upper airways and activate the body's immune response. Rhinoviruses are the most frequent cause, but they are not the only viruses responsible. The symptoms reflect a combination of viral activity and the body's reaction to infection.
This explainer examines the sequence and duration of cold symptoms, the effects of inflammation, how rhinoviruses enter cells, and which mechanisms remain uncertain. It draws on the review by Heikkinen and Järvinen (2003), nasal biopsy findings from Winther et al. (1984), and experiments by Naclerio et al. (1988) and Turner et al. (1998).

Evidence last checked 13 Nov 2026 · 12 min
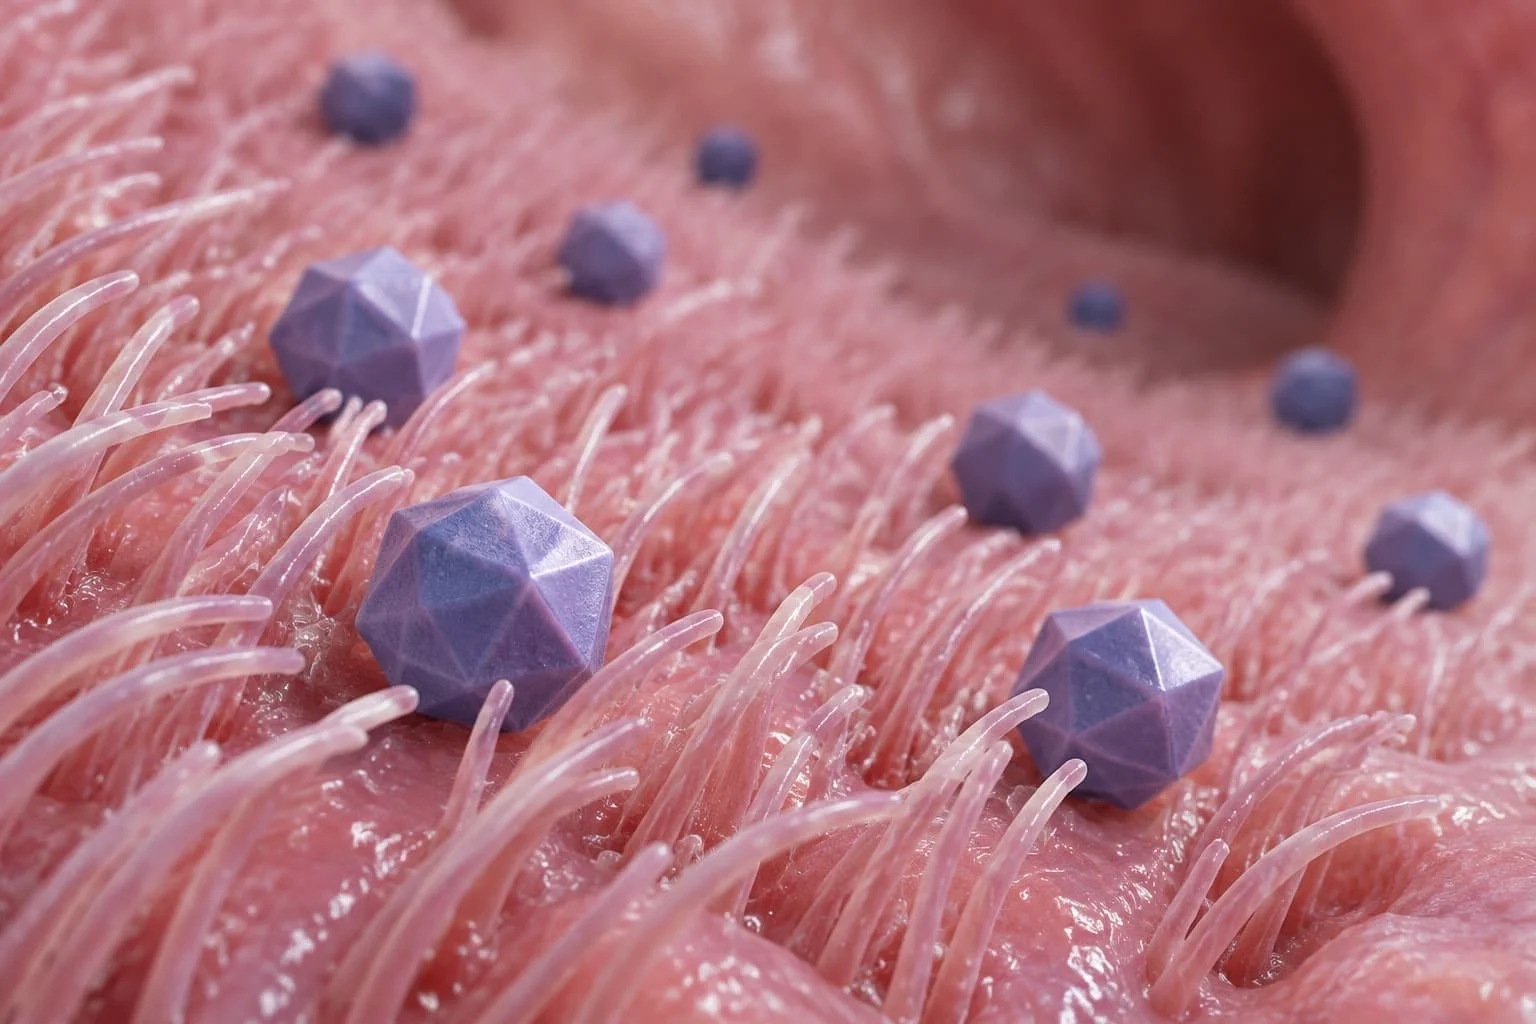
What are the symptoms of a cold, and in what order do they appear?
The common cold is an acute infection of the upper respiratory tract. Its most recognisable features are nasal discharge, congestion, sneezing, sore throat and cough. Symptoms usually concentrate around the nose and throat, although the sinuses and middle ear can also be affected. Their combination and severity vary with the virus and the individual (Heikkinen and Järvinen, 2003).
A rhinovirus infection often begins with a scratchy or sore throat. Nasal discharge, sneezing and congestion may follow, with cough developing or becoming more noticeable later. This is a typical pattern rather than a fixed sequence: not everyone experiences every symptom, and some symptoms can appear close together.
Research has also identified differences between early and later symptoms. Headache, sneezing, chilliness and a general feeling of being unwell may develop relatively quickly and begin to subside after a day or two. Nasal discharge, obstruction and cough can become more prominent over the following days (Eccles, 2005).
The symptoms have different physiological origins:
- A sore throat can result when inflammatory mediators stimulate sensory nerve endings in the throat.
- Sneezing is a reflex involving sensory nerves in the nasal lining and neural pathways that coordinate the respiratory muscles.
- A runny nose reflects increased glandular secretion, fluid movement from local blood vessels and reflex responses to irritation.
- Nasal congestion develops when blood vessels and venous spaces in the nasal lining become swollen, narrowing the passages through which air flows.
- Cough can occur when inflammation makes sensory nerve endings in the larynx and airways more sensitive.
- Headache, muscle discomfort and malaise are associated with inflammatory signalling that extends beyond the immediate site of infection (Eccles, 2005; Eccles, 2023).
Nasal discharge can change as the illness progresses. It often begins as a clear, watery fluid and may later become thicker, yellow or green. This change is associated with the arrival of white blood cells, particularly neutrophils, in the airway mucus. An enzyme in these cells, myeloperoxidase, contributes to the colour.
Coloured mucus does not, by itself, establish that a bacterial infection has developed. The appearance of nasal discharge needs to be considered in the wider context of the illness rather than treated as proof of a particular cause (Heikkinen and Järvinen, 2003; Eccles, 2005).
Fever is less characteristic of rhinovirus colds in adults than of some other respiratory infections. Children may develop fever more often during upper respiratory infections. A person can nevertheless experience headache, tiredness and muscle discomfort without having a raised temperature.
How long does a cold last, and when do symptoms peak?
The timing of a cold varies, but symptoms usually develop over several days rather than appearing all at once. The interval between infection and the first symptoms is known as the incubation period.
In experimental studies, symptoms have sometimes appeared within 10–12 hours of intranasal exposure. Such observations come from controlled research conditions and should not be taken as the usual timeline for everyday infections (Heikkinen and Järvinen, 2003).
For many people, symptoms become more noticeable during the first few days and reach their greatest intensity around days two or three. They then tend to ease gradually. A typical cold lasts about 7–10 days, although this is an approximate range rather than a deadline by which every symptom must disappear (Heikkinen and Järvinen, 2003).
Stage | Typical pattern |
Incubation | The virus is establishing infection; symptoms have not yet appeared |
Early illness | Throat irritation, sneezing or a general feeling of being unwell may begin |
First few days | Symptoms often intensify; nasal discharge and congestion become prominent |
Following days | Early symptoms may ease while nasal symptoms and cough continue |
Around days 7–10 | Many people have substantially improved |
Longer recovery | Cough or residual symptoms may persist beyond the main illness |
Note: the stages above describe a typical course recorded in challenge studies and reviews, not a schedule that every cold follows. Timing varies between people and between viruses.
Not all symptoms follow the same course. A sore throat or general malaise may settle relatively early, while nasal congestion and cough can last longer. Eccles (2005) describes cough persisting for three weeks or more in some cases. This difference reflects the fact that symptoms involve several tissues and inflammatory pathways, which do not necessarily return to normal at the same rate.
Public health descriptions sometimes give slightly different estimates for how long a cold lasts. This can reflect whether the measure is the period of feeling generally unwell or the time until the final symptom has disappeared. The key point is that improvement is usually gradual, and a lingering cough does not necessarily mean that every aspect of the infection is still at its peak.
Why does a cold make you feel ill if the virus barely damages your nose?
Rhinoviruses infect epithelial cells, which form the surface lining of the respiratory tract. Yet studies of nasal tissue have found that extensive structural destruction is generally absent during common colds. This creates an important distinction between the amount of visible tissue damage and the severity of the symptoms a person experiences.
Winther et al. (1984) examined nasal biopsy specimens from people with naturally acquired colds. Although some epithelial cells were shed, the lining generally remained continuous and its structure was largely preserved. The researchers also observed an increase in neutrophils in the epithelium and underlying tissue.
The findings suggest that a cold does not need to destroy large areas of the nasal lining to cause substantial discomfort. Instead, infection activates immune signalling in the relatively small number of cells that detect or contain the virus. These signals influence nearby tissue and recruit immune cells, creating a broader response than the initial infection alone might suggest.
Arruda et al. (1995) used in situ hybridisation to locate rhinovirus replication in the upper respiratory tract. Viral material was detected in infected subjects, but only a small proportion of nasal epithelial cells contained detectable viral material. This provides further context for the mismatch between the extent of infection and the experience of symptoms.
This helps explain why symptoms are not simply a direct measure of how many cells the virus has infected. The body's response is an important part of the illness.
Which inflammatory mediators contribute to cold symptoms?
Inflammation is coordinated by signalling molecules that help cells detect infection, communicate with one another and recruit immune defences. Researchers have measured several such mediators in nasal secretions during experimental rhinovirus colds. These include kinins, interleukins and other inflammatory substances.
Bradykinin is one of the mediators studied in relation to nasal and throat symptoms. It can influence blood vessels and stimulate sensory nerve endings. In an experimental rhinovirus study, Naclerio et al. (1988) found increased kinin concentrations in participants who developed symptomatic infections. The changes were associated with other indicators of inflammation, including neutrophil numbers in nasal secretions.
A separate experiment examined the effects of bradykinin introduced into the nose. The researchers observed rhinitis symptoms and sore throat, alongside measurable changes in nasal obstruction (Proud et al., 1988). This demonstrates that bradykinin can reproduce some symptoms under experimental conditions. It does not prove that it is the sole or dominant cause of those symptoms during a naturally acquired cold.
Interleukin-8, also known as CXCL8, has a different role. It helps recruit neutrophils to sites of inflammation. Turner et al. (1998) found that IL-8 concentrations in nasal secretions were higher in symptomatic participants with experimental rhinovirus infections than in asymptomatic infected participants or controls. Changes in IL-8 were also associated with the severity of nasal obstruction and discharge.
Other cytokines, including interleukin-1, interleukin-6 and tumour necrosis factor, participate in wider immune signalling. They are associated with systemic features such as fever, headache, malaise and muscle discomfort. The relationship between individual mediators and individual symptoms is complex: several signals can act together, and one mediator may affect more than one tissue or process (Eccles, 2005; Eccles, 2023).
These findings support the view that inflammation contributes substantially to the common cold. They do not establish that every symptom can be attributed to one molecule or pathway.
How does a rhinovirus get inside a cell?
Rhinoviruses belong to the genus Enterovirus in the family Picornaviridae. They are non-enveloped viruses with a single-stranded, positive-sense RNA genome enclosed in a protein capsid.
To infect a cell, a rhinovirus must first attach to a suitable receptor on its surface. Different rhinovirus groups use different receptors, which helps explain some of the biological differences between them.
The major group uses intercellular adhesion molecule-1, or ICAM-1. Greve et al. (1989) identified this cell-surface protein as the major human rhinovirus receptor. A smaller group uses members of the low-density lipoprotein receptor family, as demonstrated by Hofer et al. (1994).
Rhinoviruses are divided into three species: A, B and C (Eccles, 2023). Rhinovirus C uses a different receptor, cadherin-related family member 3 (CDHR3). Bochkov et al. (2015) showed that CDHR3 can enable rhinovirus C binding and replication in experimental cells that would otherwise be unsusceptible.
The receptor is therefore not just a point of attachment. It is part of the process that determines whether a particular cell can be infected by a particular rhinovirus group.
How a respiratory virus moves between people is a separate question from how it causes symptoms. The account of [how RSV spreads](/health/how-rsv-spreads-lessons-from-a-1981-transmission-study-health/) examines transmission rather than the inflammatory mechanisms behind cold symptoms.
Symptoms involving the chest can raise different diagnostic questions from those associated with a typical cold. An overview of [chest disease diagnosis](/health/chest-disease-diagnosis-radiologic-signs-differential-health/) describes how imaging findings contribute to evaluating chest conditions.
Why does the common cold virus prefer the nose?
The nasal cavity provides an environment in which many rhinoviruses can replicate efficiently. One proposed factor is temperature. The nose is cooler than the body's core. Many rhinovirus isolates replicate more efficiently at temperatures around 33–35 °C than at 37 °C (Foxman et al., 2015).
This difference may be related not only to the virus but also to the way host cells defend themselves. In laboratory experiments, Foxman et al. (2015) found that mouse airway cells mounted stronger innate antiviral responses at 37 °C than at 33 °C. These findings suggest that cooler conditions can make it easier for some rhinoviruses to evade or overcome parts of the local antiviral response.
However, temperature is not a complete explanation. Rhinovirus types differ, and some can replicate at higher temperatures. The virus is also capable of infecting cells beyond the nose. The cooler nasal environment may favour replication by many rhinoviruses, but it does not mean that infection is restricted to the upper airways.
Does everyone who catches a rhinovirus get symptoms?
No. Infection and symptomatic illness are not identical. Some people exposed to rhinovirus develop recognisable cold symptoms, while others may have an infection without a noticeable illness.
Experimental studies distinguish between participants who become infected and those who develop symptoms. This distinction is important when interpreting research on immune responses: an infected person without symptoms may still show evidence of viral activity, but their response does not produce the same clinical picture.
The likelihood and severity of symptoms can vary with several factors, including prior immunity, the virus type and characteristics of the person exposed. A review by Eccles (2023) discusses research into susceptibility, including studies of sleep and other behavioural or environmental associations. These findings concern the probability of developing illness after exposure; they should not be interpreted as proof that any single factor determines whether an individual will catch a cold.
The contrast with a virus that can be vaccinated against is instructive. The history of that effort is set out in the account of [the present status of polio vaccines](/health/the-present-status-of-polio-vaccines-health/).
What does the evidence settle, and what remains uncertain?
Human studies provide strong evidence that rhinovirus infection does not usually cause widespread structural destruction of the nasal epithelium. Biopsy studies and investigations of viral localisation have found relatively limited visible damage, even in people with symptoms (Winther et al., 1984; Arruda et al., 1995).
There is also substantial evidence that inflammatory activity accompanies symptomatic infection. Kinins and IL-8 have been measured in nasal secretions, and experimental exposure to bradykinin can reproduce some cold-like symptoms (Naclerio et al., 1988; Proud et al., 1988; Turner et al., 1998).
However, evidence that a mediator is associated with symptoms is not the same as proof that it causes them. Intervention studies illustrate this limitation. Higgins et al. (1990) tested a bradykinin antagonist in volunteers with rhinovirus infections but did not find the expected relief of cold symptoms. In another experimental study, reducing nasal kinin concentrations did not produce a significant reduction in overall symptom scores, and viral titres were higher in the treated group (Gustafson et al., 1996).
Nor does the absence of visible tissue destruction mean that the virus has no direct effect on the airway. Sajjan et al. (2008) found that rhinovirus infection could disrupt the barrier function of airway epithelial cells in laboratory and animal models. The effect involved changes to tight-junction organisation and did not require cell death. How fully this finding translates to naturally acquired human colds remains uncertain.
The most balanced conclusion is that inflammation probably makes a substantial contribution to common cold symptoms, while direct viral effects and interactions between several immune pathways may also matter. The precise contribution of each mechanism has not been established.
Research question | Current conclusion | Evidence strength |
Does rhinovirus extensively destroy the nasal lining? | Widespread structural destruction is generally absent in human biopsy studies | Strong |
Does inflammation accompany symptomatic infection? | Several inflammatory mediators increase and correlate with symptom severity | Moderate to strong |
Can bradykinin reproduce cold-like symptoms? | It can produce some symptoms experimentally, but intervention studies complicate a simple causal explanation | Moderate |
Does temperature affect rhinovirus replication? | Many isolates favour cooler conditions, but the effect varies between types and models | Moderate |
Does inflammation explain every symptom? | The relative contributions of inflammatory and direct viral effects remain unresolved | Moderate |
The central distinction is between what researchers have observed and what they infer from those observations. Limited visible damage to the nasal lining is well supported. The idea that the immune response accounts for much of the discomfort is plausible and supported by several lines of evidence, but it is not a complete explanation of every symptom.
Frequently asked questions
How long do cold symptoms last?
Many common colds improve within about 7–10 days, although the duration varies. Some symptoms settle earlier than others: a sore throat or general malaise may ease while congestion continues. Cough can persist for three weeks or longer in some people, so the last symptom may outlast the main period of illness.
What is usually the first symptom of a cold?
A scratchy or sore throat is a common early symptom of rhinovirus infection. Sneezing and nasal symptoms may follow, but there is no universal sequence. Some people notice a runny nose or congestion first, and not everyone develops every symptom associated with a common cold.
Why do you get a blocked nose during a cold?
Inflammation changes the blood vessels and tissues lining the nasal passages. Blood vessels and venous spaces become swollen, reducing the space available for airflow. Increased mucus secretion also contributes to the sensation of blockage. The symptom is therefore linked to changes in the nasal lining, not simply to mucus filling the nose.
Can you have a rhinovirus infection without symptoms?
Yes. Infection does not always lead to noticeable illness. Research distinguishes between people who become infected and those who develop symptoms after exposure. A person may have evidence of infection without experiencing the familiar combination of sneezing, sore throat, nasal discharge and congestion.
Is a cold or flu worse, and how do you tell them apart?
A cold usually develops gradually and mainly affects the nose and throat. Influenza more often begins suddenly and can cause pronounced fever, headache, muscle aches and weakness, although symptoms overlap. Neither pattern is universal, and symptoms alone cannot always identify the virus responsible.
Does going out in the cold cause a cold?
No. A common cold is caused by a respiratory virus, not by low outdoor temperatures themselves. Rhinoviruses can replicate efficiently in the cooler environment of the nose, but this does not mean that simply feeling cold creates an infection. Exposure to an infectious virus is required.
Sources
- Heikkinen T, Järvinen A. The common cold. The Lancet. 2003;361(9351):51–59. DOI 10.1016/S0140-6736(03)12162-9.
- Eccles R. Understanding the symptoms of the common cold and influenza. The Lancet Infectious Diseases. 2005;5(11):718–725. DOI 10.1016/S1473-3099(05)70270-X.
- Eccles R. Common cold. Frontiers in Allergy. 2023;4:1224988. DOI 10.3389/falgy.2023.1224988.
- Winther B, Brofeldt S, Christensen B, Mygind N. Light and scanning electron microscopy of nasal biopsy material from patients with naturally acquired common colds. Acta Oto-Laryngologica. 1984;97(3–4):309–318. DOI 10.3109/00016488409130994.
- Arruda E, Boyle TR, Winther B, Pevear DC, Gwaltney JM, Hayden FG. Localization of human rhinovirus replication in the upper respiratory tract by in situ hybridization. The Journal of Infectious Diseases. 1995;171(5):1329–1333. DOI 10.1093/infdis/171.5.1329.
- Naclerio RM, Proud D, Lichtenstein LM, et al. Kinins are generated during experimental rhinovirus colds. The Journal of Infectious Diseases. 1988;157(1):133–142. DOI 10.1093/infdis/157.1.133.
- Proud D, Reynolds CJ, Lacapra S, et al. Nasal provocation with bradykinin induces symptoms of rhinitis and a sore throat. The American Review of Respiratory Disease. 1988;137(3):613–616. DOI 10.1164/ajrccm/137.3.613.
- Turner RB, Weingand KW, Yeh CH, Leedy DW. Association between interleukin-8 concentration in nasal secretions and severity of symptoms of experimental rhinovirus colds. Clinical Infectious Diseases. 1998;26(4):840–846. DOI 10.1086/513922.
- Higgins PG, Barrow GI, Tyrrell DA. A study of the efficacy of the bradykinin antagonist, NPC 567, in rhinovirus infections in human volunteers. Antiviral Research. 1990;14(6):339–344. DOI 10.1016/0166-3542(90)90052-9.
- Gustafson LM, Proud D, Hendley JO, Hayden FG, Gwaltney JM. Oral prednisone therapy in experimental rhinovirus infections. The Journal of Allergy and Clinical Immunology. 1996;97(4):1009–1014. DOI 10.1016/S0091-6749(96)80077-7.
- Greve JM, Davis G, Meyer AM, et al. The major human rhinovirus receptor is ICAM-1. Cell. 1989;56(5):839–847. DOI 10.1016/0092-8674(89)90688-0.
- Hofer F, Gruenberger M, Kowalski H, et al. Members of the low density lipoprotein receptor family mediate cell entry of a minor-group common cold virus. Proceedings of the National Academy of Sciences of the United States of America. 1994;91(5):1839–1842. DOI 10.1073/pnas.91.5.1839.
- Bochkov YA, Watters K, Ashraf S, et al. Cadherin-related family member 3, a childhood asthma susceptibility gene product, mediates rhinovirus C binding and replication. Proceedings of the National Academy of Sciences of the United States of America. 2015;112(17):5485–5490. DOI 10.1073/pnas.1421178112.
- Foxman EF, Storer JA, Fitzgerald ME, et al. Temperature-dependent innate defense against the common cold virus limits viral replication at warm temperature in mouse airway cells. Proceedings of the National Academy of Sciences of the United States of America. 2015;112(3):827–832. DOI 10.1073/pnas.1411030112.
- Sajjan U, Wang Q, Zhao Y, Gruenert DC, Hershenson MB. Rhinovirus disrupts the barrier function of polarized airway epithelial cells. American Journal of Respiratory and Critical Care Medicine. 2008;178(12):1271–1281. DOI 10.1164/rccm.200801-136OC.

Elias Norford — author,editor
Elias trained in biomedical science before completing postgraduate study in epidemiology, where he developed a particular interest in study design, population risk, disease surveillance and the interpretation of health data. He later moved into non-clinical re...
This article is for general information and is not medical advice. It was reviewed for accuracy by a qualified clinician; decisions about your health should be made with your own doctor.
Related

How RSV spreads: lessons from a 1981 transmission study

Polio vaccines in 1960: what the debate got right and wrong
Chest disease diagnosis: radiologic signs and differentials
How hepatitis B spreads and why some infections become chronic
How staph infections start on the skin and reach the blood

How Cardiolipin Helped Standardize Syphilis Serology

Partner Violence and Condom Use in HIV-Discordant Couples
