

















Why vitamin A deficiency remains a leading cause of child blindness
The link between vitamin A deficiency and childhood blindness involves the light-sensitive retinal pigment as well as the condition of the conjunctival and corneal membranes, both of which require the nutrient (NIH ODS, 2025). A shortage may first interfere with seeing in darkness; extensive corneal injury can subsequently leave scars that permanently affect sight (Gilbert, 2013).
Food access and infection can coincide. Stevens and colleagues (2015) estimated nutritional deficiency from surveys, while Imdad and colleagues (2022) reviewed trials of preventive supplementation assessing illness and mortality outcomes. These approaches do not measure the same event as an examination identifying a child with vision loss.

Evidence last checked 19 Nov 2026 · 13 min
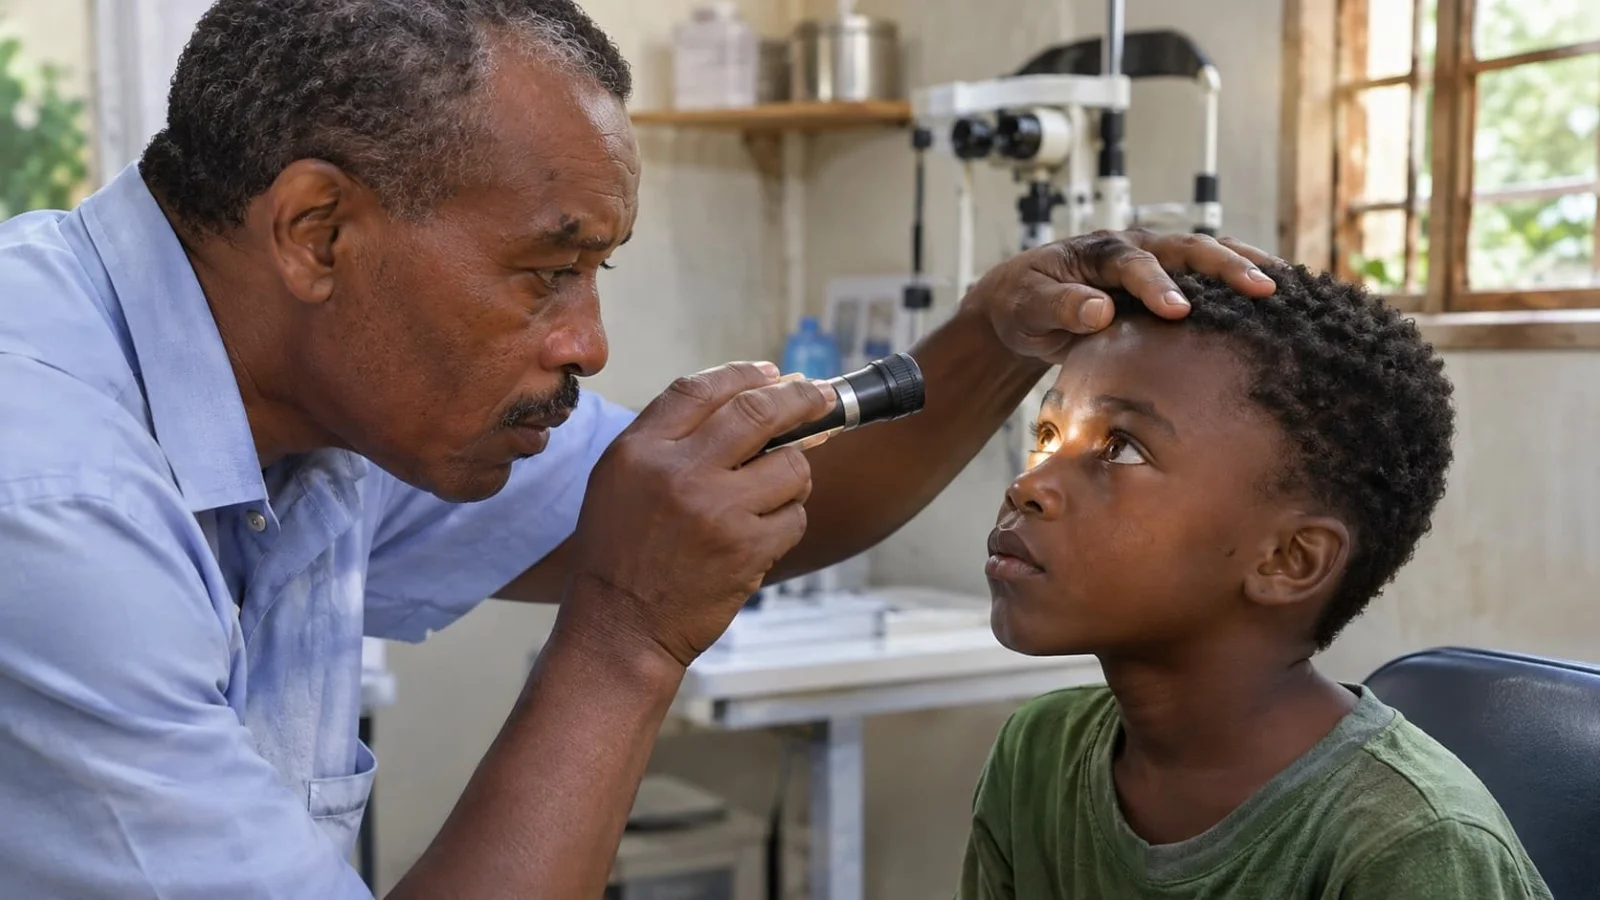
What vitamin A deficiency is and which children are at risk
The term vitamin A deficiency refers to a shortage of compounds needed for retinoid-dependent functions, including vision and maintenance of the ocular surface. Human diets supply these compounds along two pathways: retinol or retinyl esters present in animal-derived foods, and plant carotenoids that undergo conversion inside the intestine (NIH ODS, 2025).
Dietary vitamin A and body stores
Obtaining vitamin A depends on diet because the human body cannot manufacture it independently, as Choi and colleagues (2021) explain. The NIH ODS (2025) separates dietary retinol from carotenoid precursors, which must first undergo intestinal conversion.
Liver, fish, eggs and milk products are listed among concentrated sources of preformed vitamin A in the NIH ODS fact sheet (2025). Plant-derived provitamin A follows another biochemical path. In the intestine, BCMO1 carries out the conversion that makes vitamin A available from carotenoids. A food's composition, however, is not itself a measurement of the person's vitamin A stores.
Childhood vulnerability and geographical patterns
Vitamin A reserves are already a concern at birth for infants born prematurely: the NIH ODS (2025) describes low hepatic stores and persistently low circulating retinol during infancy. Later childhood brings different constraints, including insufficient nutrition accompanied by frequent infection in settings with limited resources (Patil et al., 2023). The age-specific circumstances are not interchangeable.
To estimate the scale of deficiency, Stevens and colleagues (2015) assembled 134 population-representative datasets measuring serum retinol across 83 countries and fitted a Bayesian hierarchical model. For children aged 6–59 months in low-income and middle-income countries, the resulting model put prevalence at 39% in 1991 and 29% in 2013.
Stevens and colleagues (2015) placed the proportion of deficient children in 2013 at 48% for sub-Saharan Africa and 44% for South Asia. These historical modelled proportions concern nutritional status, without measuring the present-day frequency of childhood blindness.
Using estimates of sight loss for 2017, Xu and colleagues (2021) found that age-specific prevalence and years-lived-with-disability rates peaked in the post-neonatal age group (28–364 days). South Asia had the highest age-standardised prevalence rate among the seven GBD super-regions, while Central Sub-Saharan Africa had the highest rates among the more detailed GBD regions. Stevens and colleagues (2015) investigated a different outcome by modelling the frequency of deficient serum-retinol status from population surveys, without directly counting blindness cases.
Vitamin A deficiency symptoms from night blindness to corneal injury
The visual system has separate dependencies on this nutrient. Within the retina, it contributes to sensing faint light; at the front of the eye, it sustains the normal function of the conjunctival lining and corneal tissue (NIH ODS, 2025). Gilbert's (2013) clinical descriptions range from impaired night vision and visible conjunctival changes to destruction of the cornea in severe disease.
Night blindness and Bitot spots
Night vision may decline without any visible lesion. The light-detection chemistry detailed by the NIH ODS (2025) and Choi and colleagues (2021) relies on vitamin A-derived components of retinal pigments, providing a biochemical explanation for poor vision after dark. Gilbert (2013) describes deficient children who show no obvious abnormality of the eye. Night blindness also has other causes, including cataracts and retinal disorders such as retinitis pigmentosa (American Academy of Ophthalmology, 2018).
Bitot spots mark the conjunctiva. Gilbert (2013) places the small, raised lesions with their white, frothy appearance on the bulbar conjunctiva near the limbus, where an examiner can observe them directly. The NIH ODS (2025) describes a separate retinal role for this nutrient in sensing light, which accounts for a functional symptom such as night blindness.
For population surveillance, the WHO (2014) treats night blindness and xerophthalmia as clinical indicators of inadequate vitamin A status. Its guidance identifies two purposes for recording how often they occur: following changes over time and assessing the impact of interventions.
Xerophthalmia and irreversible corneal damage
Xerophthalmia encompasses the spectrum of ocular manifestations of vitamin A deficiency, from night blindness and Bitot spots to severe corneal damage (WHO, 2014). Vitamin A deficiency can reduce mucin secretion by conjunctival goblet cells and may also decrease aqueous tear production. These changes destabilise the tear film and contribute to corneal dryness (Sommer, 1983).
Corneal ulceration and keratomalacia damage the tissue itself. Gilbert (2013) lists the consequences according to the extent of destruction: corneal scars, a forward-projecting damaged surface, and, in advanced cases, shrinkage of the eye. Restoration of vitamin A availability does not establish reversal of these structural injuries.
Illness may coincide with particularly rapid deterioration. Gilbert (2013) records keratomalacia after measles or diarrhoeal episodes in children who were vitamin A deficient, sometimes despite a previously healthy appearance. The observation concerns susceptible children and does not imply that every child with either infection develops corneal injury.
What causes vitamin A deficiency in children
An inadequate diet is one cause. The NIH ODS (2025) connects such restricted access in developing countries with poverty and customary diets. In resource-poor settings, Patil and colleagues (2023) also describe nutritional inadequacy alongside recurrent intestinal infections and chronic inflammation.
Inadequate intake and limited food access
Foods contain two kinds of vitamin A sources. Liver, fish, eggs and dairy supply preformed vitamin A; plant carotenoids instead undergo conversion by intestinal BCMO1 before they provide the usable vitamin (NIH ODS, 2025).
Research on biochemical changes during a mainly fruit diet offers a separate example of how food choices and nutritional measurements can be discussed. That work does not quantify vitamin A deficiency among children. The relevant physiological distinction is between a nutrient being present in food and its subsequent absorption and storage (NIH ODS, 2025; Patil et al., 2023).
Malabsorption, infections and disturbed stores
Fat digestion matters for vitamin A uptake. Patil and colleagues (2023) link intestinal retinol absorption with pancreatic enzymes and bile, and identify pancreatic insufficiency or an operation bypassing the duodenum as causes of impaired absorption.
Patil and colleagues (2023) identify inadequate nutrition compounded by recurrent gut infections and chronic inflammation as a prominent cause of deficiency in resource-limited settings. Infection also changes blood retinol. The NIH ODS (2025) notes that concentrations can fall during illness, so a single test may reflect inflammation as well as nutritional status.
Gilbert (2013) describes an especially severe clinical sequence in already deficient children who develop keratomalacia after measles, with the infection contributing to depletion of vitamin A stores. This account shows how infection and pre-existing nutritional vulnerability can meet. It does not establish an identical outcome for every child who contracts measles.
How vitamin A deficiency causes blindness and affects immunity
Photoreceptor pigments contain a vitamin A-derived molecule. The retinal component shifts into a different configuration under light and thereby initiates photoreceptor signalling, a molecular reaction described by Choi and colleagues (2021). The NIH ODS (2025) also identifies the conjunctival and corneal membranes as vitamin A-dependent tissues.
Rhodopsin and dark adaptation
Within retinal photoreceptors, rhodopsin functions with a vitamin A-derived molecule whose 11-cis configuration changes to all-trans when light is absorbed, a reaction set out by the NIH ODS (2025) and Choi and colleagues (2021). That change begins photoreceptor signalling (Choi et al., 2021).
After exposure to light, photoreceptor opsins regain sensitivity by receiving regenerated 11-cis-retinal, which the visual cycle produces through the enzymatic reactions described by Choi and colleagues (2021). The repeated need for this retinoid supplies a direct biochemical connection between vitamin A availability and adaptation to low light.
Corneal epithelium and immune barriers
The conjunctiva and cornea depend on vitamin A for normal surface function (NIH ODS, 2025). Deficiency can impair mucin-producing conjunctival goblet cells and reduce aqueous tears, destabilising the tear film and increasing corneal dryness (Sommer, 1983).
Clinical deterioration need not be gradual. Children with existing deficiency have developed keratomalacia after bouts of diarrhoea or measles in the cases discussed by Gilbert (2013).
Some consequences involve mortality. Stevens and colleagues' (2015) model attributed 94,500 diarrhoeal deaths and 11,200 measles deaths in 2013 to deficiency.
How vitamin A deficiency is diagnosed
Two kinds of evidence are available. WHO guidance (2014) examines xerophthalmia and night blindness when assessing clinical deficiency across populations. The NIH ODS (2025) describes a different measurement problem: blood retinol can remain stable while liver reserves are depleted, and can fall because of infection.
Clinical eye findings and serum retinol
Bitot spots are one observable lesion. In Gilbert's (2013) clinical description, the slightly raised foamy conjunctival changes appear alongside a range of other possible signs, including dryness, ulceration and the severe tissue breakdown known as keratomalacia. No fixed sequence is required.
In its 2025 professional fact sheet, the NIH ODS associates a serum or plasma retinol concentration of 20 mcg/dL (0.70 micromoles/L) or less with moderate deficiency in many cases. That laboratory indicator is not equivalent to a direct inventory of liver vitamin A. The same source notes that stored reserves may already be nearly exhausted before a fall becomes evident in the bloodstream.
Monitoring programmes can use the frequency of xerophthalmia and night blindness to follow deficiency across populations, as the WHO stated in 2014. This approach has a clinical limitation: Gilbert (2013) describes children with nutritional deficiency whose eyes and vision nevertheless appear normal. Visible signs cannot capture the entire affected group.
How inflammation affects vitamin A measurements
Serum retinol is an imperfect indicator of vitamin A stores. The WHO (2012) explains that infection and inflammation may lower circulating retinol, while liver reserves can be depleted without an immediate fall in blood concentrations. The NIH ODS (2025) likewise notes that retinol results must be interpreted alongside the clinical and inflammatory context.
Across 22 nationally representative surveys, Larson and colleagues (2018) assessed the effect of including inflammatory markers in analyses of retinol and retinol-binding protein. The markers were C-reactive protein and alpha-1-acid glycoprotein. Regression adjustment produced prevalence figures 22.1 to 6.0 percentage points below those calculated without it.
Accounting for inflammatory markers alters the estimate drawn from a survey. Larson and colleagues (2018) warned that omitting this adjustment can overstate the population burden of inadequate vitamin A status.
How vitamin A deficiency is treated and prevented
In Gilbert's (2013) clinical description, children already deficient in vitamin A developed keratomalacia following measles or episodes of diarrhoea, sometimes after previously appearing relatively healthy. The WHO (2014) uses the prevalence of night blindness to monitor trends in populations.
Deaths from all causes were measured in preventive supplementation trials. A pooled analysis by Imdad and colleagues (2022) indicated lower mortality, but the mortality result in individually randomised trials reviewed by Bjelakovic and colleagues (2024) was not statistically significant.
Clinical care and food-based approaches
The clinical distinction between altered vision and damaged tissue matters when interpreting recovery. Choi and colleagues (2021) explain the retinal pigment reaction involved in seeing in dim light, while Gilbert (2013) records scarring after advanced corneal injury. Improving vitamin A availability does not prove that a structurally destroyed cornea can return to its previous condition.
The diet contains preformed vitamin A in foods such as liver, fish, eggs and dairy, alongside plant carotenoids that must undergo conversion before supplying the nutrient, as described by the NIH ODS (2025). Patil and colleagues (2023) identify pancreatic function and bile-related fat digestion among the processes influencing uptake.
Another food-composition example appears in research on vitamin C changes in peas after shipping, freezing and canning. That research is about a different vitamin and does not quantify childhood vitamin A deficiency. For vitamin A, the established distinction is between dietary chemical forms, their absorption and stored nutrient availability (NIH ODS, 2025; Patil et al., 2023).
Supplementation and fortification programmes
The review covered many distinct endpoints. Imdad and colleagues (2022) collected 47 studies with approximately 1,223,856 children in 19 countries, considering mortality and illness alongside night blindness and Bitot spots. Separate analyses used different numbers of studies for their outcome estimates.
Fortification addresses the composition of foods rather than the treatment of an already damaged eye. The NIH ODS (2025) describes the nutrient's dietary forms and its role in vision, but does not provide a corresponding estimate of childhood blindness prevented through fortification. Results of supplementation trials cannot establish that missing figure.
Adverse outcomes were recorded alongside possible benefits. Imdad and colleagues' (2022) trials found increased vomiting during the first 48 hours after supplementation, with RR 1.97 and a 95% confidence interval of 1.44 to 2.69.
What clinical trials and population studies found
The analysis of all-cause mortality published by Imdad and colleagues (2022) in their Cochrane update brought together findings from 19 trials and a total of 1,202,382 children across the eligible comparisons. The estimated risk ratio was 0.88, its 95% confidence interval running from 0.83 to 0.93; the authors described an observed 12% reduction against control.
Two trials enrolling 22,972 children gave RR 0.32 for the prevalence of night blindness, while five trials covering 1,063,278 children gave RR 0.42 for the prevalence of Bitot spots (Imdad et al., 2022). Neither outcome measures how an established corneal scar responds to treatment.
Bjelakovic and colleagues (2024) separated individually randomised evidence from trials randomised by cluster. Among 78 individually randomised trials with 178,094 participants, the childhood mortality comparison was not statistically significant: RR 0.96, 95% confidence interval 0.88 to 1.04. In the 15 cluster-randomised trials (14 in children and one in adults; 364,343 participants), the mortality risk ratio was 0.84 (95% confidence interval 0.76 to 0.93), although the certainty of this evidence was considered very low.
Study | Evidence examined | Result | Interpretation |
Stevens et al., 2015 | Population-representative data from 83 countries | Estimated deficiency prevalence among children aged 6–59 months in 138 low-income and middle-income countries was 29% in 2013 | A modelled nutritional prevalence measure, not the prevalence of blindness |
Imdad et al., 2022 | 19 trials, 1,202,382 children | All-cause mortality RR 0.88, 95% confidence interval 0.83 to 0.93 | Preventive supplementation compared with control |
Imdad et al., 2022 | 2 trials, 22,972 children | Night blindness prevalence RR 0.32, 95% confidence interval 0.21 to 0.50 | Prevalence of night blindness, not recovery of damaged corneas |
Bjelakovic et al., 2024 | 78 individually randomised trials, 178,094 participants | Child mortality RR 0.96, 95% confidence interval 0.88 to 1.04 | No statistically significant effect in this analysis |
Larson et al., 2018 | 22 nationally representative surveys | Adjustment reduced estimated deficiency prevalence by 22.1 to 6.0 percentage points | Inflammatory markers change population estimates |
The Cochrane mortality finding concerned 19 trials, whereas the later review found no statistically significant mortality effect in its individually randomised comparisons (Imdad et al., 2022; Bjelakovic et al., 2024). Bjelakovic and colleagues (2024) also described the effect on blindness as uncertain in their evidence base. Mortality comparisons cannot by themselves resolve whether supplementation reverses corneal damage already present.
What is proven about vitamin A deficiency and what is not
The best-established ocular mechanisms involve photopigment function and the maintenance of surface tissues. Retinoids participate in restoration of retinal sensitivity, while extensive corneal disease may produce lasting anatomical injury (NIH ODS, 2025; Choi et al., 2021; Gilbert, 2013). Gilbert (2013) also warns that some children with deficient stores have no visible eye abnormalities, even though deficiency can lead to blindness.
The retina depends on vitamin A to respond to light, and severe deficiency can leave the cornea permanently scarred. Prevention trials report changes in specific outcomes, but their results do not yield one reliable count of blindness cases averted (Gilbert, 2013; Imdad et al., 2022; Bjelakovic et al., 2024).
Gilbert (2013) found that eye signs may be absent. During infection, circulating retinol may also decline independently of what a single blood measurement can reveal about storage (NIH ODS, 2025). Larson and colleagues (2018) showed that adjustments for inflammation altered national prevalence estimates, demonstrating a substantial problem in interpreting such surveys.
Each endpoint has a distinct evidence base. Imdad and colleagues (2022) reported lower all-cause mortality and lower prevalence of night blindness and Bitot spots in their supplementation analyses. By contrast, Bjelakovic and colleagues' (2024) individually randomised mortality result was statistically non-significant and their conclusion on blindness remained uncertain.
The studies answer separate questions. Gilbert (2013) describes permanent eye injury, Stevens and colleagues (2015) modelled deficiency prevalence, and Bjelakovic and colleagues (2024) considered blindness effects uncertain. Trials with comparable ophthalmic outcomes, baseline nutrient status and infection data would be needed to quantify prevention of childhood blindness directly.
Frequently asked questions
Can eyesight recover after vitamin A deficiency?
Night blindness caused by vitamin A deficiency is generally reversible when vitamin A status is restored (WHO, 2012). Retinal light sensitivity depends on vitamin A-derived pigment in the visual cycle (Choi et al., 2021). Severe corneal ulceration or keratomalacia, however, may produce permanent scarring and vision loss despite correction of the deficiency (Gilbert, 2013).
Does night blindness always mean vitamin A deficiency?
Night blindness can occur with vitamin A deficiency because vitamin A-derived retinoids are needed for rhodopsin and the visual cycle (NIH ODS, 2025; Choi et al., 2021). However, conditions such as retinitis pigmentosa and cataracts can also impair night vision (American Academy of Ophthalmology, 2018). Night blindness alone therefore does not establish vitamin A deficiency.
Which foods contain retinol and provitamin A carotenoids?
The NIH ODS (2025) lists liver, fish, eggs and dairy products as foods containing preformed vitamin A, while plant carotenoids supply precursors that first undergo intestinal conversion before they become vitamin A. Patil and colleagues (2023) explain that bile and pancreatic function are relevant to the absorption of this fat-soluble nutrient.
Can vitamin A deficiency occur in high-income countries?
Deficiency is not confined to places with limited food access. Patil and colleagues (2023) describe conditions that disrupt fat digestion or intestinal absorption and can therefore restrict uptake of vitamin A. The NIH ODS (2025) also identifies low liver stores among premature infants. Regional prevalence figures do not describe every group in high-income settings.
Why can an infection change blood vitamin A results?
A retinol measurement taken during infection may reflect the inflammatory response, because the NIH ODS (2025) reports lower circulating concentrations even though this blood test cannot directly determine how much vitamin A remains stored in the liver. In national survey data, Larson and colleagues (2018) found lower estimated deficiency prevalence after adjusting for inflammation.
Sources
- National Institutes of Health, Office of Dietary Supplements. Vitamin A and Carotenoids: Fact Sheet for Health Professionals. 10 March 2025. https://ods.od.nih.gov/factsheets/VitaminA-HealthProfessional/
- World Health Organization. Xerophthalmia and night blindness for the assessment of clinical vitamin A deficiency in individuals and populations. Technical document WHO/NMH/NHD/EPG/14.4. 24 September 2014. https://www.who.int/publications-detail-redirect/WHO-NMH-NHD-EPG-14.4
- Gilbert C. The eye signs of vitamin A deficiency. Community Eye Health. 2013;26(84):66–67. DOI 10.56920/cehj.679.
- Larson LM, Guo J, Williams AM, et al. Approaches to Assess Vitamin A Status in Settings of Inflammation: Biomarkers Reflecting Inflammation and Nutritional Determinants of Anemia (BRINDA) Project. Nutrients. 2018;10(8):1100. DOI 10.3390/nu10081100.
- Imdad A, Mayo-Wilson E, Haykal MR, et al. Vitamin A supplementation for preventing morbidity and mortality in children from six months to five years of age. Cochrane Database of Systematic Reviews. 2022;(3):CD008524. DOI 10.1002/14651858.CD008524.pub4.
- Stevens GA, Bennett JE, Hennocq Q, et al. Trends and mortality effects of vitamin A deficiency in children in 138 low-income and middle-income countries between 1991 and 2013: a pooled analysis of population-based surveys. The Lancet Global Health. 2015;3(9):e528–e536. DOI 10.1016/S2214-109X(15)00039-X.
- Choi EH, Daruwalla A, Suh S, Leinonen H, Palczewski K. Retinoids in the visual cycle: role of the retinal G protein-coupled receptor. Journal of Lipid Research. 2021;62:100040. DOI 10.1194/jlr.TR120000850.
- Patil S, Zamwar UM, Mudey A. Etiology, Epidemiology, Pathophysiology, Signs and Symptoms, Evaluation, and Treatment of Vitamin A (Retinol) Deficiency. Cureus. 2023;15(11):e49011. DOI 10.7759/cureus.49011.
- Bjelakovic G, Nikolova D, Bjelakovic M, et al. Effects of primary or secondary prevention with vitamin A supplementation on clinically important outcomes: a systematic review of randomised clinical trials with meta-analysis and trial sequential analysis. BMJ Open. 2024;14(5):e078053. DOI 10.1136/bmjopen-2023-078053.
- Xu Y, Shan Y, Lin X, et al. Global patterns in vision loss burden due to vitamin A deficiency from 1990 to 2017. Public Health Nutrition. 2021;24(17):5786–5794. DOI 10.1017/S1368980021001324.
- World Health Organization. Report: Priorities in the assessment of vitamin A and iron status in populations, Panama City, Panama, 15–17 September 2010. Geneva: WHO; 2012. https://www.who.int/publications-detail-redirect/9789241504225
- Sommer A. Effects of vitamin A deficiency on the ocular surface. Ophthalmology. 1983;90(6):592–600. DOI 10.1016/S0161-6420(83)34512-7. https://pubmed.ncbi.nlm.nih.gov/6604247/
- American Academy of Ophthalmology. Night Vision. 19 December 2018. https://www.aao.org/eye-health/diseases/night-vision.

Daniel K. Reynolds — author
Daniel K. Reynolds is an independent nutrition writer with academic training in nutritional sciences and food science. His background combines nutrition research literacy with food-composition analysis and public-facing science communication. He focuses on how...
This article is for general information and is not medical advice. It was reviewed for accuracy by a qualified clinician; decisions about your health should be made with your own doctor.
Related

Mainly fruit diet study: biochemical effects in 1971

Vitamin C in Peas: Effects of Shipping, Freezing and Canning

Sport Nutrition: Energy, Fuel and Athletic Performance

What research shows about whether creatine is bad for your kidneys

Magnesium for anxiety and what the clinical trials actually found

What antioxidants are and why more is not always better

Whether creatine causes hair loss and what the DHT study found
